
English version see below
6.9 Neuroinflammation
Angesichts der Komplexität der Untersuchungsergebnisse im Tryptophan-Metabolom kann ich hier nur grundsätzliche Empfehlungen aussprechen. Diese nehmen Bezug auf die unter „Diagnostik“ in Kapitel 5.7 genannte Urinuntersuchung des Gehirnstoffwechsels (sogenanntes Tryptophan-Metabolom). Sollten andere Werte vorliegen, z. B. Blutuntersuchungen, muss man die Empfehlungen ggf. anpassen.
Tryptophan
Bei einem Tryptophanmangel schaut man, ob eher der Weg zum Serotonin, oder der zur Quinolinsäure betroffen ist. Bei ersterem empfiehlt sich die Gabe von 5-Hydroxytryptophan (5-HTP), bei letzterem die Gabe von Tryptophan.
Erinnern Sie sich: Tryptophan kann in zwei Richtungen metabolisiert werden:
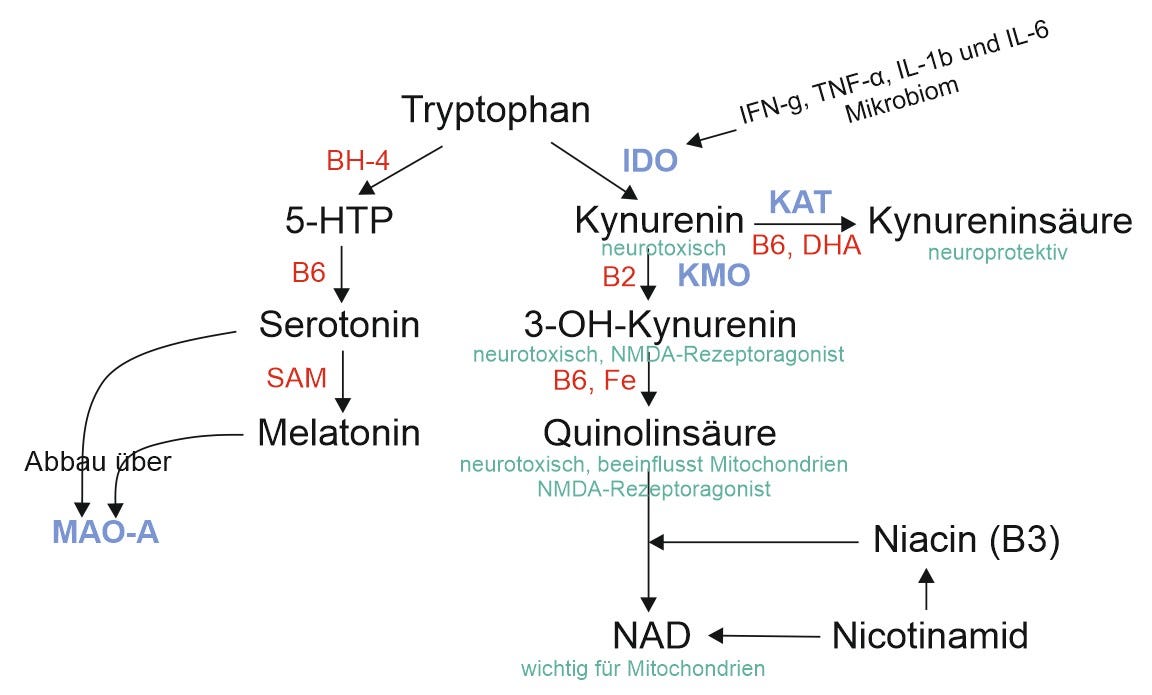
Abbildung: Tryptophanstoffwechsel. blau: zuständige Enzyme rot: Cofaktoren, grün: Auswirkungen auf Gehirn
Da der Großteil der Metabolisierung (etwa 95%) in Richtung Kynurenin und nur ca 5% über 5-HTP zur Serotoninherstellung geht, sollte man bei der Tryptophan-Substitution vorsichtig vorgehen. So kann man z. B. bei einem Serotoninmangel statt Tryptophan besser 5-HTP geben, weil man dadurch die Metabolisierung in Richtung Quinolin (NMDA-Agonist, im Überschuss neurotoxisch) nicht beeeinflusst.
Sind jedoch Kynurenin und Quinolinsäure im Mangel, ist die Gabe von Tryptophan sinnvoll, ggf. ergänzt durch die Kofaktoren Vitamin B2, B6 und Eisen.
Dosierung:
Tryptophan 500 mg bis 1.000 mg zur Nacht oder
5-HTP 200 mg einmal täglich
Höhere Dosierungen sind möglich, allerdings muss man dann das Serotonin im Auge behalten. In seltenen Fällen kann es bei einem zu hohen Serotonin-Spiegel zu einem Serotonin-Syndrom kommen. Zwar ist dies in der Regel eine Folge von zu hoher Dosierung von Antidepressiva der Gruppen SSRI, SNRI oder MAO-Inhibitoren, ist bei hoher Tryptophan- oder 5-HTP-Gabe aber theoretisch möglich, vor allem, wenn gleichzeitig Antidepressiva eingenommen werden. Ich empfehle in diesen Fällen die schrittweise Reduktion der Antidepressiva und zunächst nur niedrig dosierte Gabe von TRP oder 5-HTP.
Übrigens, während 5-HTP problemlos die Blut-Hirn-Schranke durchdringen kann, konkurriert Tryptophan mit anderen Aminosäuren am Aminosäure-Transporter der Blut-Hirn-Schranke. Darum ist es sinnvoll, Tryptophan spätabends einzunehmen, wenn die anderen durch die Nahrung aufgenommenen Aminosäuren bereits soweit notwendig ins Gehirn transportiert wurden. Dann hat Tryptophan keine Konkurrenz und wird in höherer Menge auch im Gehirn ankommen.
Quinolinsäure
Mängel, so sie denn ausgeprägt sind, z. B. bei den Cofaktoren oder B-Vitaminen, können substituiert werden. Allerdings sehe ich einen Mangel an Quinolinsäure nur sehr selten, entweder bei sehr ausgeprägtem Tryptophanmangel (Resorptionsstörung im Darm?) oder bei massiver Schwäche der Enzyme IDO oder KMO. Therapie ist hier die Gabe von Tryptophan und den Cofaktoren Vitamin B2, B6 und Eisen.
Ein Überangebot an Quinolinsäure kann man mit NMDA-Antagonisten behandeln, z. B. Dextrometorphan (in Deutschland in manchen Hustensäften enthalten). Man beginnt mit 4 mg Dextrometorphan, kann dies aber steigern.
Dosierung Dextrometorphan: 4 – 8 mg einmal täglich
IDO und KMO
Um Quinolinsäure und Kynureninsäure bilden zu können, muss Tryptophan in Kynurenin umgewandelt werden. Die dafür nötigen Enzyme IDO und TDO lassen sich (wenn in Unterfunktion) durch Indol-3-Carbinol (I3C) anregen, einem Ah-Rezeptor-Agonisten, der in Brokkoli, Grünkohl oder Rosenkohl vorkommt und dem antioxidative, antikarzinogene und antiatherogene Wirkungen zugeschrieben werden.
Dosierung
Indol-3-Carbinol 200 bis 400 mg pro Tag.
Sind IDO und/oder KMO überaktiv, sollte man sie bremsen. Hierzu sind Berberin, Curcumin und Omega-3-Fettsäuren mit hohem DHA-Anteil (Docosahexaensäure) geeignet
Dosierungen
Berberin 2 x 500 mg täglich
Curcumin etwa 1000 mg z. B. in drei Einzeldosen (3 x 350 mg) mit Piperin oder etwa 500 mg z. B. 3 x 150 mg Curcumin als liposomale Formulierung.
Omega-3-Fettsäuren (mit viel DHA) 2 bis 4 Gramm pro Tag, verteilt auf mehrere Einzeldosen
GABA

Bei einem Mangel an Gamma-Aminobuttersäure kommen eine therapeutische Gabe von GABA oder eine Modulation des GABA-Rezeptors in Betracht. Zur Rezeptormodulation eignen sich Passionsblumen- oder Baldrianpräparate. Baldrianpräparate sollten vor allem abends gegeben werden, da sie stärker sedierend wirken als Passionsblumenpräparate. Ist gleichzeitig Glutamin oder Glutamat erniedrigt, ist die Gabe von Glutamin oder Glutamat oft die bessere Lösung.
Dosierung:
GABA 500-1000 mg zur Nacht, kann bis zur Gabe von 3 x 1000 mg gesteigert werden.
Passionsblumenextrakt je nach Konzentration 350 bis etwa 750 mg
Glutamin 750 bis 3000 mg pro Tag
Mitochondrien im Gehirnstoffwechsel
Energielosigkeit kann auch auf mitochondrialen Ursachen beruhen, etwa auf einem Mangel an NAD (Nicotinamidadenindinukleotid). Auch oxidativer oder nitrosativer Stress ausgelöst durch eine stressinduzierte Silent Inflammation können eine mitochondriale Dysfunktion hervorrufen. Hierdurch sinkt die mitochondriale ATP-Produktion z. T. beträchtlich.
Ist eine mitochondriale Belastung des Gehirnstoffwechsels erkennbar (Anstieg von Laktat und Pyruvat, Citrat, eventuell auch Mangel an L-Carnitin), sollte man dies wie bei mitochondrialer Dysfunktion therapieren und wenn möglich, die Ursachen behandeln (oxidativer und nitrosativer Stress, Mangel an Kynureninsäure, NAD+ oder L-Carnitin).
Ein Mangel an L-Carnitin kann man an erhöhter Suberinsäure erkennen.
Sind Hinweise auf eine Aktivierung des zerebralen Immunsystems (erhöhtes Neopterin als Hinweis für eine INF-γ-vermittelte TH1-Aktivierung des Immunsystems) vorhanden oder besteht ein Mangel an Tryptophan, Tyrosin und Phenylalanin, wäre es sinnvoll, einmal das Mikrobiom, also die Darmflora, zu untersuchen und bei Dysbiose mit zu therapieren.
Nitrosativer Stress
Citrullin und Citrat lassen Rückschlüsse auf nitrosativen Stress zu. Ein Anstieg von Citrullin spricht für eine erhöhte NO-Synthese aus Arginin, womit eben auch Stickstoffmonoxid (NO) ansteigt. NO kann durch die folgende Bildung von Peroxynitrit nitrosativen Stress auslösen.
Steigende Citrat-Werte hingegen lassen auf eine folgende mitochondriale Fehlfunktion schließen.
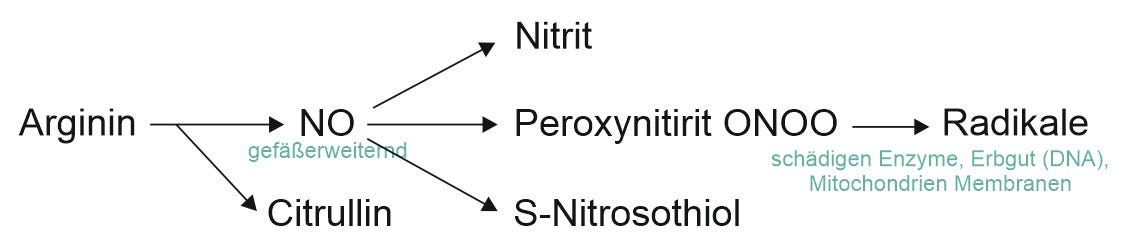
Methylmalonsäure ist ein funktioneller Marker für einen Mangel an Vitamin B12, das als NO-Gegenspieler imstande ist, die Blockade eisenhaltiger Enzyme durch NO zu lösen. Eine Erhöhung der Methylmalonsäure sollte mit Vitamin B12 behandelt werden.
Neurotransmitter
Die Katecholamine Dopamin, Noradrenalin und Adrenalin sind wichtige Neurotransmitter. Sie können in der Nervenzelle aus der Aminosäure Tyrosin gebildet werden. Tyrosin seinerseits kann aus Phenylalanin entstehen. Ein Mangel der Neurotransmitter kann somit durch die Supplementierung von Tyrosin oder Phenylalanin verbessert werden, gegebenenfalls unter Zugabe der Cofaktoren. Insbesondere niedrige Methylgruppendonatoren (S-Adenyl-Methionin = SAM, Betain und Cholin) können den Adrenalinspiegel senken
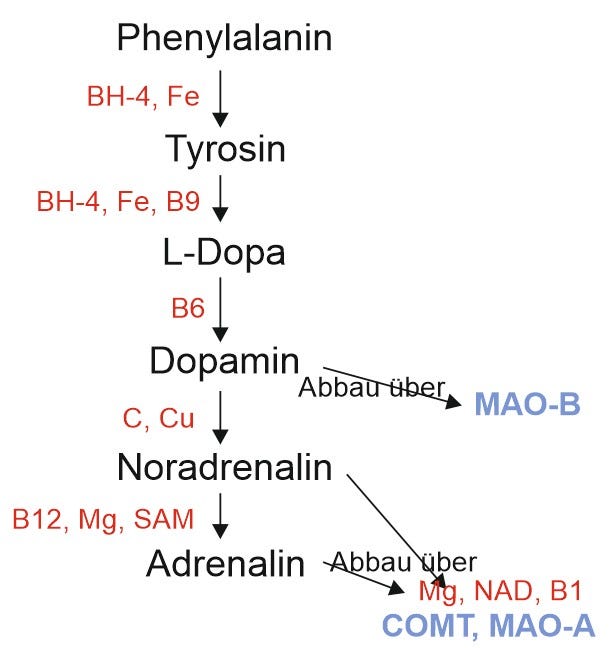
Adrenalin wird nach seiner Freisetzung durch die Catechol-O-Methyltransferase (COMT) zu Metanephrin und durch die Monoaminooxidase (MAO) zu Vanillinmandelsäure abgebaut. Zur Senkung erhöhter Adrenalinwerte kann versucht werden Kofaktoren der abbauenden Enzyme einzusetzen. Hierzu gehören vor allem Magnesium (Mg) sowie NAD und Vitamin B1.
Es ist geplant, ca. ein bis zweimal pro Woche ein neues Kapitel zu diesem Lehrbuch zu veröffentlichen, soweit es meine Zeit erlaubt. Es wird jeweils auf meinem deutschen Telegram-Kanal https://t.me/coronawissenschaft angekündigt.
Bleiben Sie neugierig
Teil 1 des Lehrbuchs finden sie hier: https://ralftillenburg.substack.com/p/lehrbuch-zur-behandlung-von-schaden
6.9 Neuroinflammation
Given the complexity of the test results in the tryptophan metabolome, I can only offer general recommendations here. These refer to the urine test for brain metabolism (known as the tryptophan metabolome) mentioned under “Diagnostics” in Chapter 5.7. If other test results are available—such as blood tests—the recommendations may need to be adjusted accordingly.
Tryptophan
In cases of tryptophan deficiency, one assesses whether the pathway to serotonin or the pathway to quinolinic acid is primarily affected. In the former case, administration of 5-hydroxytryptophan (5-HTP) is recommended; in the latter, administration of tryptophan is recommended.
Remember: Tryptophan can be metabolized in two directions:
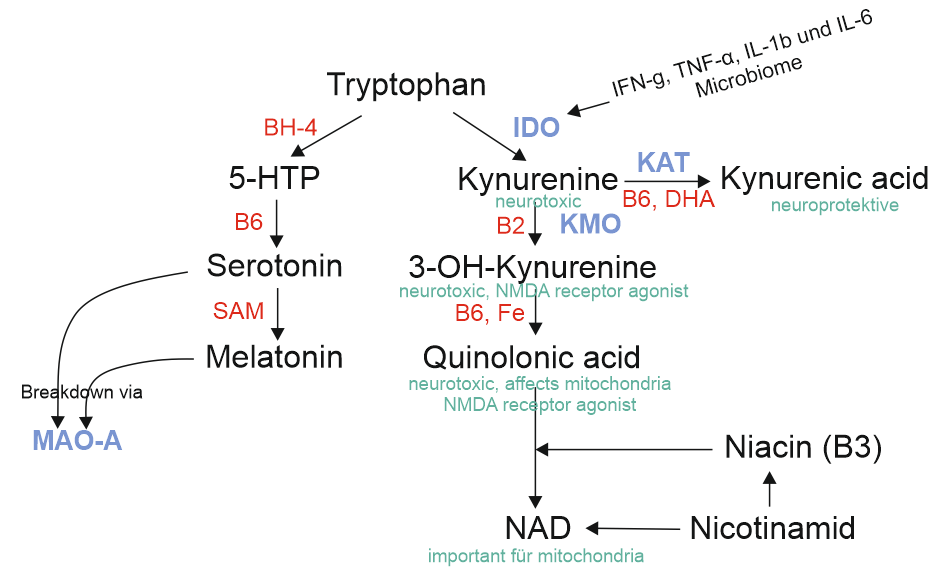
Figure: Tryptophan metabolism. Blue: relevant enzymes; red: cofactors; green: effects on the brain
Since the majority of metabolism (about 95%) proceeds toward kynurenine and only about 5% via 5-HTP for serotonin production, one should proceed with caution when administering tryptophan supplementation. For example, in cases of serotonin deficiency, it is better to administer 5-HTP instead of tryptophan, as this avoids influencing metabolism toward quinoline (an NMDA agonist that is neurotoxic in excess).
However, if there is a deficiency of kynurenine and quinolinic acid, administering tryptophan is advisable, supplemented if necessary with the cofactors vitamin B2, B6, and iron.
Dosage:
Tryptophan 500 mg to 1,000 mg at night or
5-HTP 200 mg once daily
Higher dosages are possible, but serotonin levels must be monitored closely. In rare cases, excessively high serotonin levels can lead to serotonin syndrome. Although this is usually a consequence of excessive dosing of antidepressants from the SSRI, SNRI, or MAO inhibitor classes, it is theoretically possible with high doses of tryptophan or 5-HTP, especially when taken concurrently with antidepressants. In such cases, I recommend gradually reducing the antidepressants and initially taking only low doses of TRP or 5-HTP.
Incidentally, while 5-HTP can easily cross the blood-brain barrier, tryptophan competes with other amino acids at the blood-brain barrier’s amino acid transporter. That is why it makes sense to take tryptophan late in the evening, when the other amino acids absorbed from food have already been transported to the brain as needed. Then tryptophan faces no competition and will reach the brain in greater quantities.
Quinolinic acid
Deficiencies, if they are pronounced—for example, in cofactors or B vitamins—can be corrected with supplementation. However, I very rarely see a quinoline acid deficiency—it occurs either in cases of very severe tryptophan deficiency (malabsorption in the intestine?) or in cases of severe deficiency of the enzymes IDO or KMO. Treatment in these cases involves administering tryptophan and the cofactors vitamin B2, B6, and iron.
An excess of quinolinic acid can be treated with NMDA antagonists, such as dextromethorphan (found in some cough syrups in Germany). Treatment begins with 4 mg of dextromethorphan, but the dose can be increased.
Dextromethorphan dosage: 4–8 mg once daily
IDO and KMO
In order to produce quinolinic acid and kynurenic acid, tryptophan must be converted into kynurenine. The enzymes required for this process, IDO and TDO, can be stimulated (if underactive) by indole-3-carbinol (I3C), an Ah-receptor agonist found in broccoli, kale, and Brussels sprouts, which is believed to have antioxidant, anticarcinogenic, and antiatherogenic effects.
Dosage
Indole-3-carbinol: 200 to 400 mg per day.
If IDO and/or KMO are overactive, they should be inhibited. Berberine, curcumin, and omega-3 fatty acids with a high DHA (docosahexaenoic acid) content are suitable for this purpose.
Dosages
Berberine: 2 x 500 mg daily
Curcumin: approximately 1,000 mg, e.g., in three separate doses (3 x 350 mg) with piperine, or approximately 500 mg, e.g., 3 x 150 mg curcumin as a liposomal formulation.
Omega-3 fatty acids (high in DHA): 2 to 4 grams per day, divided into several doses
GABA
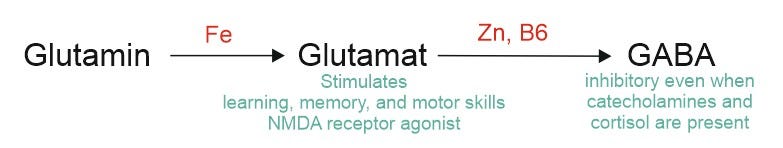
In cases of gamma-aminobutyric acid (GABA) deficiency, therapeutic administration of GABA or modulation of the GABA receptor may be considered. Passionflower or valerian preparations are suitable for receptor modulation. Valerian supplements should primarily be taken in the evening, as they have a stronger sedative effect than passionflower supplements. If glutamine or glutamate levels are also low, administering glutamine or glutamate is often the better solution.
Dosage:
GABA 500–1,000 mg at night; can be increased to 3 × 1,000 mg.
Passionflower extract: 350 to approximately 750 mg, depending on concentration
Glutamine: 750 to 3,000 mg per day
Mitochondria in Brain Metabolism
Lack of energy can also be due to mitochondrial causes, such as a deficiency in NAD (nicotinamide adenine dinucleotide). Oxidative or nitrosative stress triggered by stress-induced silent inflammation can also cause mitochondrial dysfunction. This leads to a decrease in mitochondrial ATP production, in some cases quite significant.
If mitochondrial stress on brain metabolism is evident (increased levels of lactate, pyruvate, and citrate; possibly also a deficiency in L-carnitine), it should be managed as in cases of mitochondrial dysfunction, and, if possible, the underlying causes should be addressed (oxidative and nitrosative stress, deficiency in kynurenic acid, NAD+, or L-carnitine).
A deficiency in L-carnitine can be identified by elevated levels of suberic acid.
If there are indications of activation of the cerebral immune system (elevated neopterin as an indicator of INF-γ-mediated TH1 activation of the immune system) or if there is a deficiency in tryptophan, tyrosine, and phenylalanine, it would be advisable to examine the microbiome—that is, the gut flora—and, in the event of dysbiosis, to include this in the treatment.
Nitrosative Stress
Citrulline and citrate provide insights into nitrosative stress. An increase in citrulline suggests elevated NO synthesis from arginine, which also leads to an increase in nitric oxide (NO). NO can trigger nitrosative stress through the subsequent formation of peroxynitrite.
Rising citrate levels, on the other hand, suggest subsequent mitochondrial dysfunction.
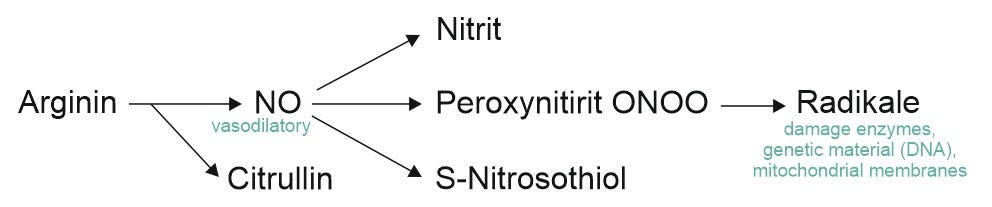
Methylmalonic acid is a functional marker for vitamin B12 deficiency; as an NO antagonist, vitamin B12 is capable of resolving the inhibition of iron-containing enzymes by NO. Elevated levels of methylmalonic acid should be treated with vitamin B12.
Neurotransmitters
The catecholamines dopamine, norepinephrine, and epinephrine are important neurotransmitters. They can be synthesized in nerve cells from the amino acid tyrosine. Tyrosine, in turn, can be derived from phenylalanine. A deficiency in these neurotransmitters can therefore be addressed by supplementing with tyrosine or phenylalanine, with the addition of cofactors as needed. In particular, low levels of methyl group donors (S-adenosylmethionine = SAM, betaine, and choline) can lower adrenaline levels
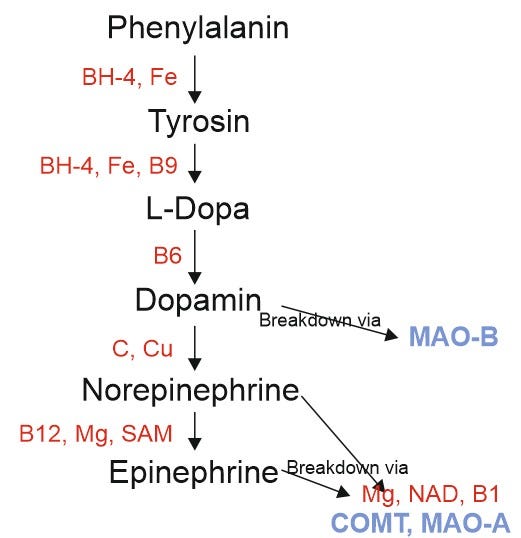
After its release, adrenaline is broken down by catechol-O-methyltransferase (COMT) into metanephrine and by monoamine oxidase (MAO) into vanillylmandelic acid. To lower elevated adrenaline levels, one can try using cofactors of the enzymes responsible for its breakdown. These include, above all, magnesium (Mg) as well as NAD and vitamin B1.
I plan to publish a new chapter of this textbook approximately once or twice a week, time permitting. Each new chapter will be announced on my German Telegram channel https://t.me/coronawissenschaft.
Stay curious
Part 1 of the textbook can be found here: https://ralftillenburg.substack.com/p/lehrbuch-zur-behandlung-von-schaden
DerPathway für das Tryptophan kann auch durch Glyphosat trächtig werden. (Shikimat Pathway), weil entsprechende Darmbakterien davon betroffen sind. Dies verwundert nicht, da der Mechanismus des Zelleintritts durch eine Art von Tiden bei den Impfungen ähnlich ist wie beim Glyphosat. Nähere Informationen gebe ich Ihnen gern separat. Einiges davon ist bereits auf meinem substack
Guten Abend, was ist bei Wahnvorstellungen… welcher Prozess ist betroffen?